What Is the Anion Gap?
The anion gap is a derived value used to evaluate acid-base balance and detect certain types of metabolic acidosis. It comes from a standard look at the body’s major electrolytes, especially the measured ions on routine blood chemistry analysis. In simple terms, the anion gap compares positively charged and negatively charged particles in the blood to determine whether there are extra unmeasured ions present.
This is important because normal physiology keeps these charges in balance. When that balance changes, it may suggest an electrolyte imbalance or a broader metabolic disturbance. The anion gap is not a diagnosis by itself. Instead, it is a screening tool that supports diagnostic interpretation in the right clinical context.
Changes in the anion gap can point to shifts in acid-base status, especially when evaluating a patient with symptoms or abnormal lab values. A high result can suggest accumulation of acids, while a low result is less common and may reflect protein changes, calculation issues, or a true shift in blood chemistry.
How to Work with an Anion Gap Calculator
An anion gap calculator based on a BMP, or basic metabolic panel, draws from routine lab results to estimate the gap fast. The standard inputs are sodium, chloride, and bicarbonate. On many reports, bicarbonate may appear as carbon dioxide, which is used as a proxy for serum bicarbonate in routine testing.
To use the calculator, enter the values from the BMP. The tool applies the formula and returns a calculated value that can be compared with the expected reference range. Because the calculation depends on serum concentrations, accuracy depends on correct entry of the serum sodium, serum chloride, and serum bicarbonate values.
This is the basic procedure:
- Identify the sodium value on the BMP. Find the chloride value on the same panel. Find the bicarbonate or carbon dioxide value. Run the calculator to compute the anion gap. Review the result with the expected normal range and interpret it alongside symptoms and other lab findings.
A calculator can make easier interpretation, but it does not substitute for clinical judgment. A result that seems abnormal may still be appropriate depending on the overall picture, including medications, hydration status, and other lab results.
Formula for Anion Gap and Expected Range
The traditional anion gap formula is:
Anion gap = sodium − (chloride + bicarbonate)
Because the calculation is based on measured ions, it estimates the gap between major cations and anions in blood. This difference represents mostly unmeasured ions, including proteins, phosphates, sulfate, and organic acids. These components help explain why the result is not zero in normal blood.
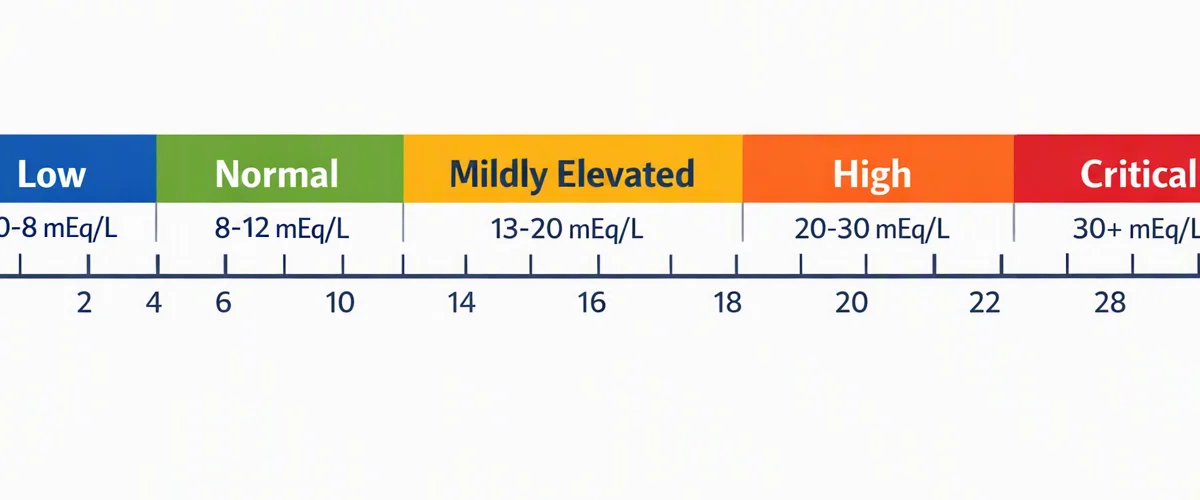
The usual normal range depends on the lab method and whether potassium is included. Many recent labs use a reference range that is more limited than older ranges, and the exact cutoff can vary by analyzer. This is why it is important to interpret the calculated value using the lab’s own reference range rather than assuming one universal number.
Albumin matters because it is a major negatively charged protein in the blood. If albumin is low, the NAGMA causes measured gap may look artificially low even if the underlying acid-base state is not normal. In those cases, clinicians may use a corrected anion gap with albumin correction to better reflect the actual state of the blood chemistry.
The anion gap is a helpful way to identify whether there may be excess acids or other unmeasured ions contributing to an abnormal result. It is especially useful when interpreting metabolic acidosis and deciding whether additional workup is needed.
What a Elevated Anion Gap Indicates
A increased anion gap may mean that additional acids are present in the blood. This result is commonly seen in metabolic acidosis, where the body has collected acids or failed to clear them efficiently. The result is not limited to one disease, but it often points toward important conditions that need prompt attention.
One major cause is lactic acidosis, which can occur when tissues do not get enough oxygen or when cells are under significant stress. Another important cause is ketoacidosis, which can develop when the body produces high levels of ketones, often during insulin deficiency, prolonged fasting, or severe illness. Both conditions increase acid levels and can raise the calculated value.
Renal failure can also cause a high result because the kidneys are less able to clear albumin corrected anion gap calculator acids and other waste products. As those substances increase, the blood chemistry changes and the anion gap may rise. This pattern can be seen with uremia, where retained metabolic products contribute to acid and base imbalance.
When the result is high, the number alone does not reveal the cause. The best interpretation comes from combining the anion gap with symptoms, other lab values, and the overall clinical context. For example, a slightly raised gap in one setting may be less urgent than the same value in a person with deep breathing, confusion, or dehydration.
What Exactly the Low Anion Gap Means
A decreased anion gap is rarer than an elevated one and can be caused by multiple issues. One of the most important is hypoalbuminemia, because low albumin decreases the amount of negatively charged protein in the blood. When albumin falls, the calculated value may also decrease, even if the rest of the electrolytes look typical.
Another cause is paraproteinemia, where abnormal proteins in the blood disturb the balance of measured and unmeasured charges. This may happen in certain plasma cell disorders and can produce an unexpectedly low result. In these situations, the anion gap is not simply a number issue; it may be an indication to a broader medical condition.
Lab error is also a common explanation for a low result. Mistakes in specimen handling, transcription, analyzer performance, or unit entry can all distort the calculation. If the value does not match the rest of the picture, repeating the BMP or reviewing the original sample may be appropriate.
Because a low result may reflect protein changes, measurement issues, or a real physiologic shift, it should not be ignored. It deserves closer consideration in the same way a high result does, especially if symptoms or other abnormal findings are present.
BMP versus Comprehensive Metabolic Panel for Anion Gap Calculation
Each of the BMP and CMP may be used in anion gap assessment, but they are not identical. A basic metabolic panel provides the key electrolytes needed for the measurement: sodium, chloride, and bicarbonate or carbon dioxide. So the BMP is the BMP the most direct and common option for an anion gap calculator.
The CMP, or complete metabolic panel, offers the same core electrolytes plus additional tests, including albumin and liver-related markers. This added information can support interpretation because albumin helps determine whether a corrected anion gap should be considered.
In practice, the electrolytes panel on a BMP is enough to calculate the raw gap, but the CMP adds important context. If albumin is low, a raw number may downplay the true abnormality. That is why the distinction between BMP and CMP matters: the BMP provides the calculation, while the CMP may help interpret the result.
For routine screening, the BMP is often adequate. For deeper interpretation, especially in suspected acid-base disorders, the CMP can provide a broader view of the patient’s blood chemistry.
Frequent Causes of Abnormal Anion Gap
An abnormal value can stem from various acid-base disorders, and the result pattern matters. A high value usually indicates excess acids or held onto acids, while a low value often reflects protein changes or measurement problems. Knowing the cause helps direct next steps.
Some frequent causes of a high result are:
- Lactic acidosis from limited oxygen delivery, shock, or severe illness Ketoacidosis from insulin deficiency, fasting, or other metabolic stress Renal failure with buildup of acid and waste products Uremia due to impaired clearance of metabolic byproducts Toxins that introduce or release acids
Salicylates are a classic toxin-related cause of abnormal acid-base findings. They can produce complex changes in breathing and metabolism and may result in a high gap. Other toxins can also alter the balance of measured and unmeasured substances in the blood.
For a low result, the main contributors are hypoalbuminemia, paraproteinemia, and lab error. In some cases, medications or unusual electrolyte patterns may also play a role. The key is to interpret the number as part of the larger diagnostic picture rather than as a stand-alone finding.
When to Consider Medical Assessment
If you have an abnormal result on a blood test, the appropriate next step depends on the number, your symptoms, and the reason the test was ordered. A slightly abnormal value may be reviewed at a subsequent visit, but a clearly abnormal result with concerning symptoms should be assessed promptly by a clinician.
Seek urgent emergency care if an abnormal result is paired with severe vomiting, rapid breathing, confusion, fainting, chest pain, marked weakness, or signs of dehydration. These symptoms can appear with serious metabolic acidosis or other acute metabolic problems.
Because the anion gap is a calculated value, it should be interpreted alongside the rest of the lab panel and the clinical presentation. A person with high anion gap acidosis may need immediate evaluation, while a person with a low anion gap may need repeat testing, albumin review, or assessment for protein abnormalities.
If you are unsure what your result means, bring the report to a clinician for review. The most useful interpretation combines the calculator result with your history, medications, physical findings, and the full set of lab values.
Frequently Asked Questions
How do you determine the anion gap from a BMP?
Use the values for sodium, chloride, and bicarbonate from the BMP. The standard formula is sodium minus the sum of chloride and bicarbonate. Many anion gap calculator tools use this same method, and some reports list bicarbonate as carbon dioxide. The result is then compared with the lab’s normal range for interpretation.
What is a normal anion gap range?
The normal range varies by laboratory and analyzer, so there is not one universal cutoff. Different labs may report slightly different ranges depending on their methods. The safest approach is to compare the calculated value with the reference interval provided by the lab that performed the BMP. Albumin level and clinical context can also affect interpretation.
Why might the anion gap to be high even if bicarbonate is only mildly low?
A increased anion gap can appear before bicarbonate drops dramatically because the gap reflects an increase in unmeasured ions and acids. In initial or mixed disorders, the bicarbonate may be only mildly low while lactic acidosis, ketoacidosis, or an additional acid load is already present. This is why the anion gap is useful for detecting metabolic acidosis that may not yet be obvious from bicarbonate alone.
Can I determine an anion gap without albumin?
Yes, you can, you can calculate the raw anion gap without albumin because the standard BMP provides the needed electrolytes. However, albumin is important for interpretation because low albumin can produce a deceptively low result. If hypoalbuminemia is present or suspected, a corrected anion gap with albumin correction may be more informative.
How should I respond if my anion gap is abnormal?
If your result is abnormal, discuss it with a clinician who can interpret it in the full clinical context. A repeat blood test may be needed if lab error is possible, and additional testing may be ordered to look for metabolic acidosis, renal failure, salicylates, uremia, or other causes. If you also have concerning symptoms, especially breathing changes, confusion, or severe weakness, seek emergency care.