What is the anion gap and why does albumin matter?
The anion gap is a calculated value from a standard electrolyte panel that helps providers evaluate acid-base disorder patterns, especially metabolic acidosis. It is derived from routine laboratory measurements, most often serum sodium, serum chloride, and serum bicarbonate. Because it is a computed number rather than a directly measured one, the anion gap is best thought of as a preliminary and diagnostic clue that needs clinical interpretation in context.
Albumin matters because it is a major unmeasured anion in blood. When albumin is low, the measured anion gap can look falsely normal or only mildly elevated even when there is serious metabolic acidosis underneath. This is a classic example of how an electrolyte imbalance can alter acid-base balance assessment. In other words, low albumin can underestimate the true severity of an acid-base problem.
This is where the anion gap calculator becomes valuable, especially when it includes a correction for hypoalbuminemia. A corrected value gives a more accurate assessment of the laboratory picture and can change the diagnosis, workup, and treatment plan. It is particularly important when there is concern for high anion gap metabolic acidosis, because a low albumin state can make the gap appear deceptively reassuring.
Common acid contributors such as lactate and ketones may be present even when the uncorrected anion gap seems normal. That is why the corrected value is often the better clinical choice than the raw number alone.
What is the adjusted anion gap formula for hypoalbuminemia?
The most often used corrected anion gap equation adjusts the measured gap higher when serum albumin concentration is below normal. The standard albumin correction factor employed in numerous clinical settings is:
Corrected anion gap = measured anion gap + 2.5 × (4.0 - serum albumin in g/dL)
This anion gap equation uses a normal albumin of 4.0 g/dL. If albumin is reported in g/dL and is under the normal range, the correction increases the gap by 2.5 mEq/L for every 1 g/dL decline below 4.0 g/dL. The result is reported in mEq/L.
For example, if the measured anion gap is 10 mEq/L and the serum albumin is 2.0 g/dL, the correction is:
- 4.0 - 2.0 = 2.0 2.0 × 2.5 = 5.0 10 + 5 = 15 mEq/L corrected
That change may move the patient from a seemingly normal reference range into a clearly elevated range, which is essential for detecting an underlying acid load. This is why the anion gap calculator should be used with care when albumin is low.
There are slightly different described correction factors in the literature, but the 2.5 mEq/L per 1 g/dL albumin decrease remains the standard and practical clinical formula for routine use in 2026. The goal is not perfect precision in every case; the goal is a better assessment of the true clinical interpretation.
How to determine the adjusted anion gap step-by-step
Using an anion gap calculator is useful, but knowing the manual calculation is necessary for reliable interpretation. The usual first step is to work out the uncorrected anion gap from the measured sodium, chloride, and bicarbonate values.
Measured anion gap = serum sodium - (serum chloride + serum bicarbonate)
Step 1: Enter the serum values from the electrolyte panel. As an example:
- Serum sodium: 140 mEq/L Serum chloride: 102 mEq/L Serum bicarbonate: 18 mEq/L Albumin: 2.4 g/dL
Step 2: Determine the measured anion gap.
140 - (102 + 18) = 140 - 120 = 20 mEq/L
Step 3: Use the albumin correction factor.
4.0 - 2.4 = 1.6
1.6 × 2.5 = 4.0
Step 4: Add the correction to the measured gap.
20 + 4.0 = 24 mEq/L corrected anion gap
The adjusted result suggests a clearer signal for high anion gap metabolic acidosis than the measured gap alone. In this example, the anion gap calculator helps reduce the risk of missing a clinically important disorder.
When you work out the gap manually, be sure the units are aligned and that the values come from the same laboratory measurement time. The most useful results come from a well-rounded clinical context, not from isolated numbers interpreted in a vacuum.
What albumin adjustment factor is used in 2026?
The practical 2026 formula still uses the same correction applied calculate delta gap broadly in modern practice: apply 2.5 mEq/L to the anion gap for each 1 g/dL decline in normal albumin below 4.0 g/dL. Albumin is expressed in g/dL, and the corrected gap is expressed in mEq/L.
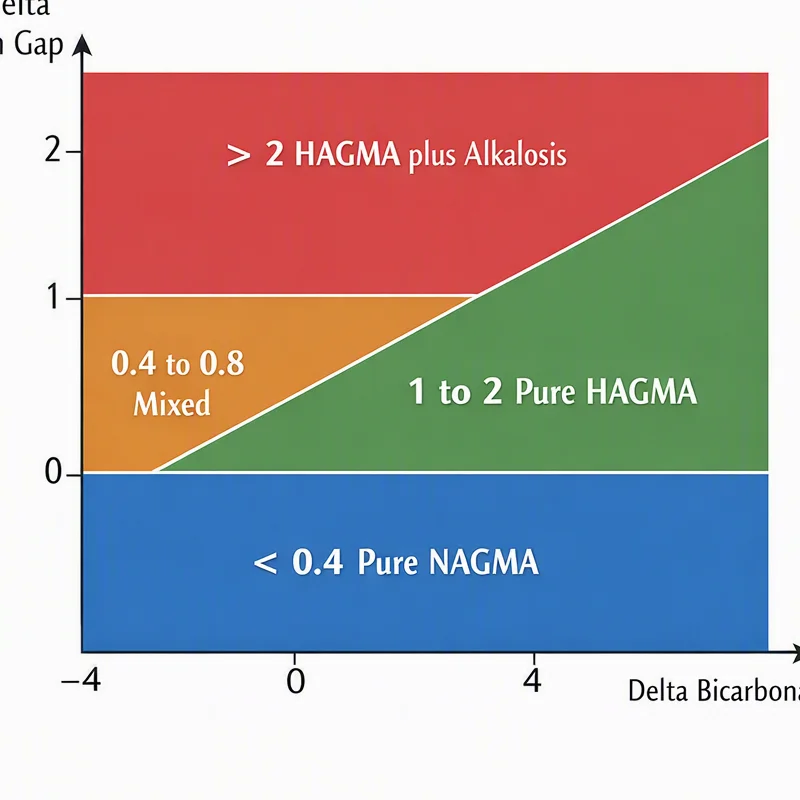
NAGMA causesThis correction continues to be favored because it is simple, quick, and readily incorporated into bedside reasoning or an automated anion gap calculator. While some sources describe alternative constants, the 2.5 factor is still the most clinically recognizable and is often the default assumption in many clinical tools.
Why does this matter in 2026? Because the core issue has not changed: a low serum albumin concentration decreases the measured anion gap and can hide the true acid-base picture. The correction improves accurate assessment of the patient’s acid burden and supports better diagnosis and evaluation.
It is also worth remembering that the correction is an approximation, not a perfect physiological measurement. It should be used as a clinical reference that improves interpretation, especially when other findings suggest a unrecognized acidosis or another acid-base disorder.
When should low albumin correction be considered?
Albumin correction for low levels should be used whenever the patient has significant hypoalbuminemia and the anion gap is being used to assess possible acid-base disorders. This is especially important in critical illness, where albumin often decreases and the laboratory picture can lead to confusion.
Situations where correction is often helpful include:
- Assessment of unexplained metabolic acidosis Potential high anion gap metabolic acidosis with a slightly abnormal measured gap Cases where the measured gap appears normal but lactate or ketones are elevated Patients with kidney disease who may have mixed acid-base issues Patients with liver disease and decreased albumin production
In kidney disease, acid retention can increase the true anion gap while albumin remains low, creating a misleadingly modest uncorrected result. In liver disease, low albumin synthesis can make the measured gap seem lower than expected. In critical illness, fluid shifts, inflammation, nutrition problems, and organ dysfunction often work together to confuse interpretation.
That said, not every patient with hypoalbuminemia requires formal correction in every situation. If the clinical question is not acid-base related, the correction may be less relevant. But if the purpose is to evaluate acidosis, the adjusted value is usually much more informative.
What is the meaning of a corrected vs uncorrected anion gap?
This distinction between corrected and uncorrected results can substantially affect clinical interpretation. A normal lab result does not always exclude a real high anion gap process if albumin is low. In contrast, a mildly elevated measured gap may appear more definitively abnormal after correction, supporting the case for organic acids such as lactate or ketones.
A measured gap in the normal range may still coexist with an acid burden if albumin is reduced. After correction, the result may fall into a clearly elevated range, uncovering a hidden acidosis interpretation that would otherwise be missed. For this reason clinicians use the corrected value to shape the diagnostic workup.
Example interpretation:
- Uncorrected normal anion gap: could still be compatible with true high-gap acidosis if albumin is low Corrected elevated anion gap: indicates a high-gap process and should prompt evaluation for lactate, ketones, toxins, or renal causes Corrected normal anion gap: indicates that the measured elevation may have been explained mainly by low albumin or that no major high-gap process is present
The relationship with base excess can also be informative. Base excess reflects metabolic severity, while the corrected anion gap helps determine whether unmeasured anions are present. When combined, they can improve acid-base balance assessment and reduce missed diagnoses.
In summary, the corrected result is often more useful clinically than the raw laboratory value, especially when evaluating suspected acid-base disturbance in the setting of low albumin.
Frequent reasons of reduced albumin and acid-base abnormalities
Low albumin is not a condition by itself; it is a signal. Several conditions can lower albumin and alter acid-base status at the same time. Recognizing the cause helps guide the workup and improve management.
Malnutrition can reduce albumin production and coexist with electrolyte imbalance, poor intake, or catabolic stress. In such cases, the measured anion gap may be lower than expected, masking metabolic changes.
Nephrotic syndrome causes urinary protein loss and can cause marked hypoalbuminemia. This can distort the measured anion gap while also being associated with kidney-related acid-base problems.
Cirrhosis and other forms of liver disease decrease albumin synthesis and often occur with fluid shifts, inflammation, and altered clearance of organic acids. The result may be a confusing laboratory picture unless the corrected anion gap is considered.
Inflammation and critical illness can lower albumin through reduced synthesis, redistribution, and increased catabolism. These states also increase the risk of lactic acidosis, sepsis-related metabolic changes, and other complex acid-base disorders.
All of these causes underline the same message: low albumin can alter the interpretation of the electrolyte panel, so a corrected approach improves diagnostic accuracy. When the clinical picture suggests acidosis, the corrected anion gap should be part of the assessment.
Frequently asked questions about the corrected anion gap formula
What is the corrected anion gap formula for low albumin?
The commonly used formula is: corrected anion gap = measured anion gap + 2.5 × (4.0 - serum albumin in g/dL). It is a practical clinical formula that adjusts for the effect of low albumin on the measured laboratory value.
Why does low albumin lower the measured anion gap?
Albumin is a major unmeasured anion in blood. When albumin falls, the measured anion gap falls too, even if other acids are present. This can cause the lab result to underestimate the severity of an acid-base problem.
Which albumin level is supposed be used for correction?
Take the patient’s present serum albumin concentration taken from the same lab test, preferably reported in g/dL. The correction is typically calculated on a typical albumin reference of 4.0 g/dL.
Does all patients with hypoalbuminemia require an anion gap correction?
No, not always. The correction is most useful when evaluating acid-base status, especially if a metabolic acidosis is suspected. If the anion gap serves for a another purpose, the correction may be unnecessary, but it is often valuable in clinical interpretation of acidosis.
How do you interpret a normal corrected anion gap in acidosis?
If the corrected gap is normal, it indicates that unmeasured anions are not driving the disorder and that the patient may have a normal anion gap metabolic acidosis or another non-gap process. In that situation, review the full acid-base picture, including bicarbonate, chloride, base excess, and the broader clinical context.